Hospitals in the U.S. - Statistics & Facts
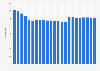
The U.S. hospital sector is navigating a structural paradox: the number of hospitals has steadily declined — from 7,156 in 1975 to 6,100 in 2024 — while total hospital care expenditure has surged to $1.5 trillion in 2023. This divergence between a contracting physical infrastructure and rising system-wide costs points to a fundamental tension: the sector is generating more revenue per facility, but the distribution of that financial capacity is increasingly uneven. For-profit hospitals represent the only ownership segment that has grown in number over recent decades, reflecting a gradual compositional shift away from non-profit and government-run facilities toward commercially oriented providers. This consolidation dynamic is also visible in M&A activity, which continues to reshape the competitive landscape through system-level integration — pointing to a sector where scale is increasingly a prerequisite for financial viability.
The Rural–Urban Divide Deepens
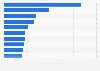
Within the overall contraction, rural hospitals bear a disproportionate share of the pressure. Over half of the net decline in community hospitals to date has been accounted for by rural facilities, and 196 rural hospitals have completely closed or been converted since 2005. The financial gap between facility types is stark: in 2023, urban community hospitals posted an operating margin of 5.4 percent, compared to just 3.1 percent for rural counterparts — with many facilities in non-micropolitan areas operating at a loss. This margin deficit reflects structurally higher dependency on Medicaid and Medicare, which reimburse at lower rates than private insurers, leaving rural hospitals with limited financial buffer. Looking ahead, 446 hospitals are identified as at risk of closing or reducing services due to Medicaid funding cuts as of 2026, threatening access for an estimated 6.6 million patients and underscoring how geographically concentrated the sector's vulnerability has become.
A Care Model in Transition, With Rising Cost Burdens
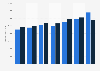
Beyond structural consolidation, a fundamental shift in how care is delivered is reshaping hospital economics. Outpatient revenue surpassed inpatient revenue in general hospitals for the first time in 2023, reaching an estimated $678 billion — consistent with outpatient visit rates rising steadily from 1.8 to 2.5 visits per person per year between 1999 and 2024. This shift is broadly efficiency-driven, but it also compresses the inpatient revenue base that traditionally cross-subsidizes higher-cost services and workforce. On the cost side, average hospital operating expenses reached $251.5 million per facility in 2023, up from $183.9 million in 2018 — with labor accounting for 60 percent of all hospital expenses, equivalent to over $1 trillion in 2025. Persistent workforce turnover, which stood at 18.3 percent in 2024, sustains recruitment and agency staffing costs that weigh directly on this dominant expense category. This combination of a declining inpatient revenue share and escalating labor costs increases the sector's sensitivity to any further disruption in payer reimbursement structures.
Sector Outlook
The U.S. hospital sector is entering a period where structural stressors are converging simultaneously, making the near-term outlook materially more complex than the revenue growth trajectory alone would suggest. The passage of the One Big Beautiful Bill Act in July 2025 — estimated by the nonpartisan Congressional Budget Office to reduce federal Medicaid spending by $911 billion over the 2025–2034 period and increase the number of uninsured Americans by 10 million by 2034 — represents the most significant policy shift affecting hospital financing in recent memory. For rural hospitals already operating on thin margins and heavily reliant on Medicaid, this funding contraction — compounded by new caps on state-directed supplemental payments that limit states' ability to offset lower federal reimbursement rates — could accelerate closures beyond what historical trends would predict. Evidence suggests that rural hospitals in Medicaid expansion states have fared measurably better financially, indicating that the policy reversal may disproportionately affect already vulnerable non-expansion markets.
At the same time, workforce instability remains an unresolved structural cost, and the continued migration to outpatient care — while operationally efficient — narrows the cross-subsidization capacity that has historically buffered lower-margin service lines. Whether the sector can preserve adequate access while absorbing these compounding pressures on both the revenue and cost sides remains uncertain.